Research library
Medicine and clinical care: completion history
All area pages | Area definition | Scoring rubric
Created November 7, 2026. The three earlier snapshots are retrospective judgment-based estimates, not scores recorded at the time. The current assessment is unchanged. Historical confidence is very low; current confidence is low. Zero can indicate an evidence gap rather than absent capability.
Chart layout updated November 8, 2026: one graph with four dated lines. Scores and assessment dates are unchanged. Overlapping lines indicate equal values; point labels show November 7, 2026. The table below contains every date's exact values.
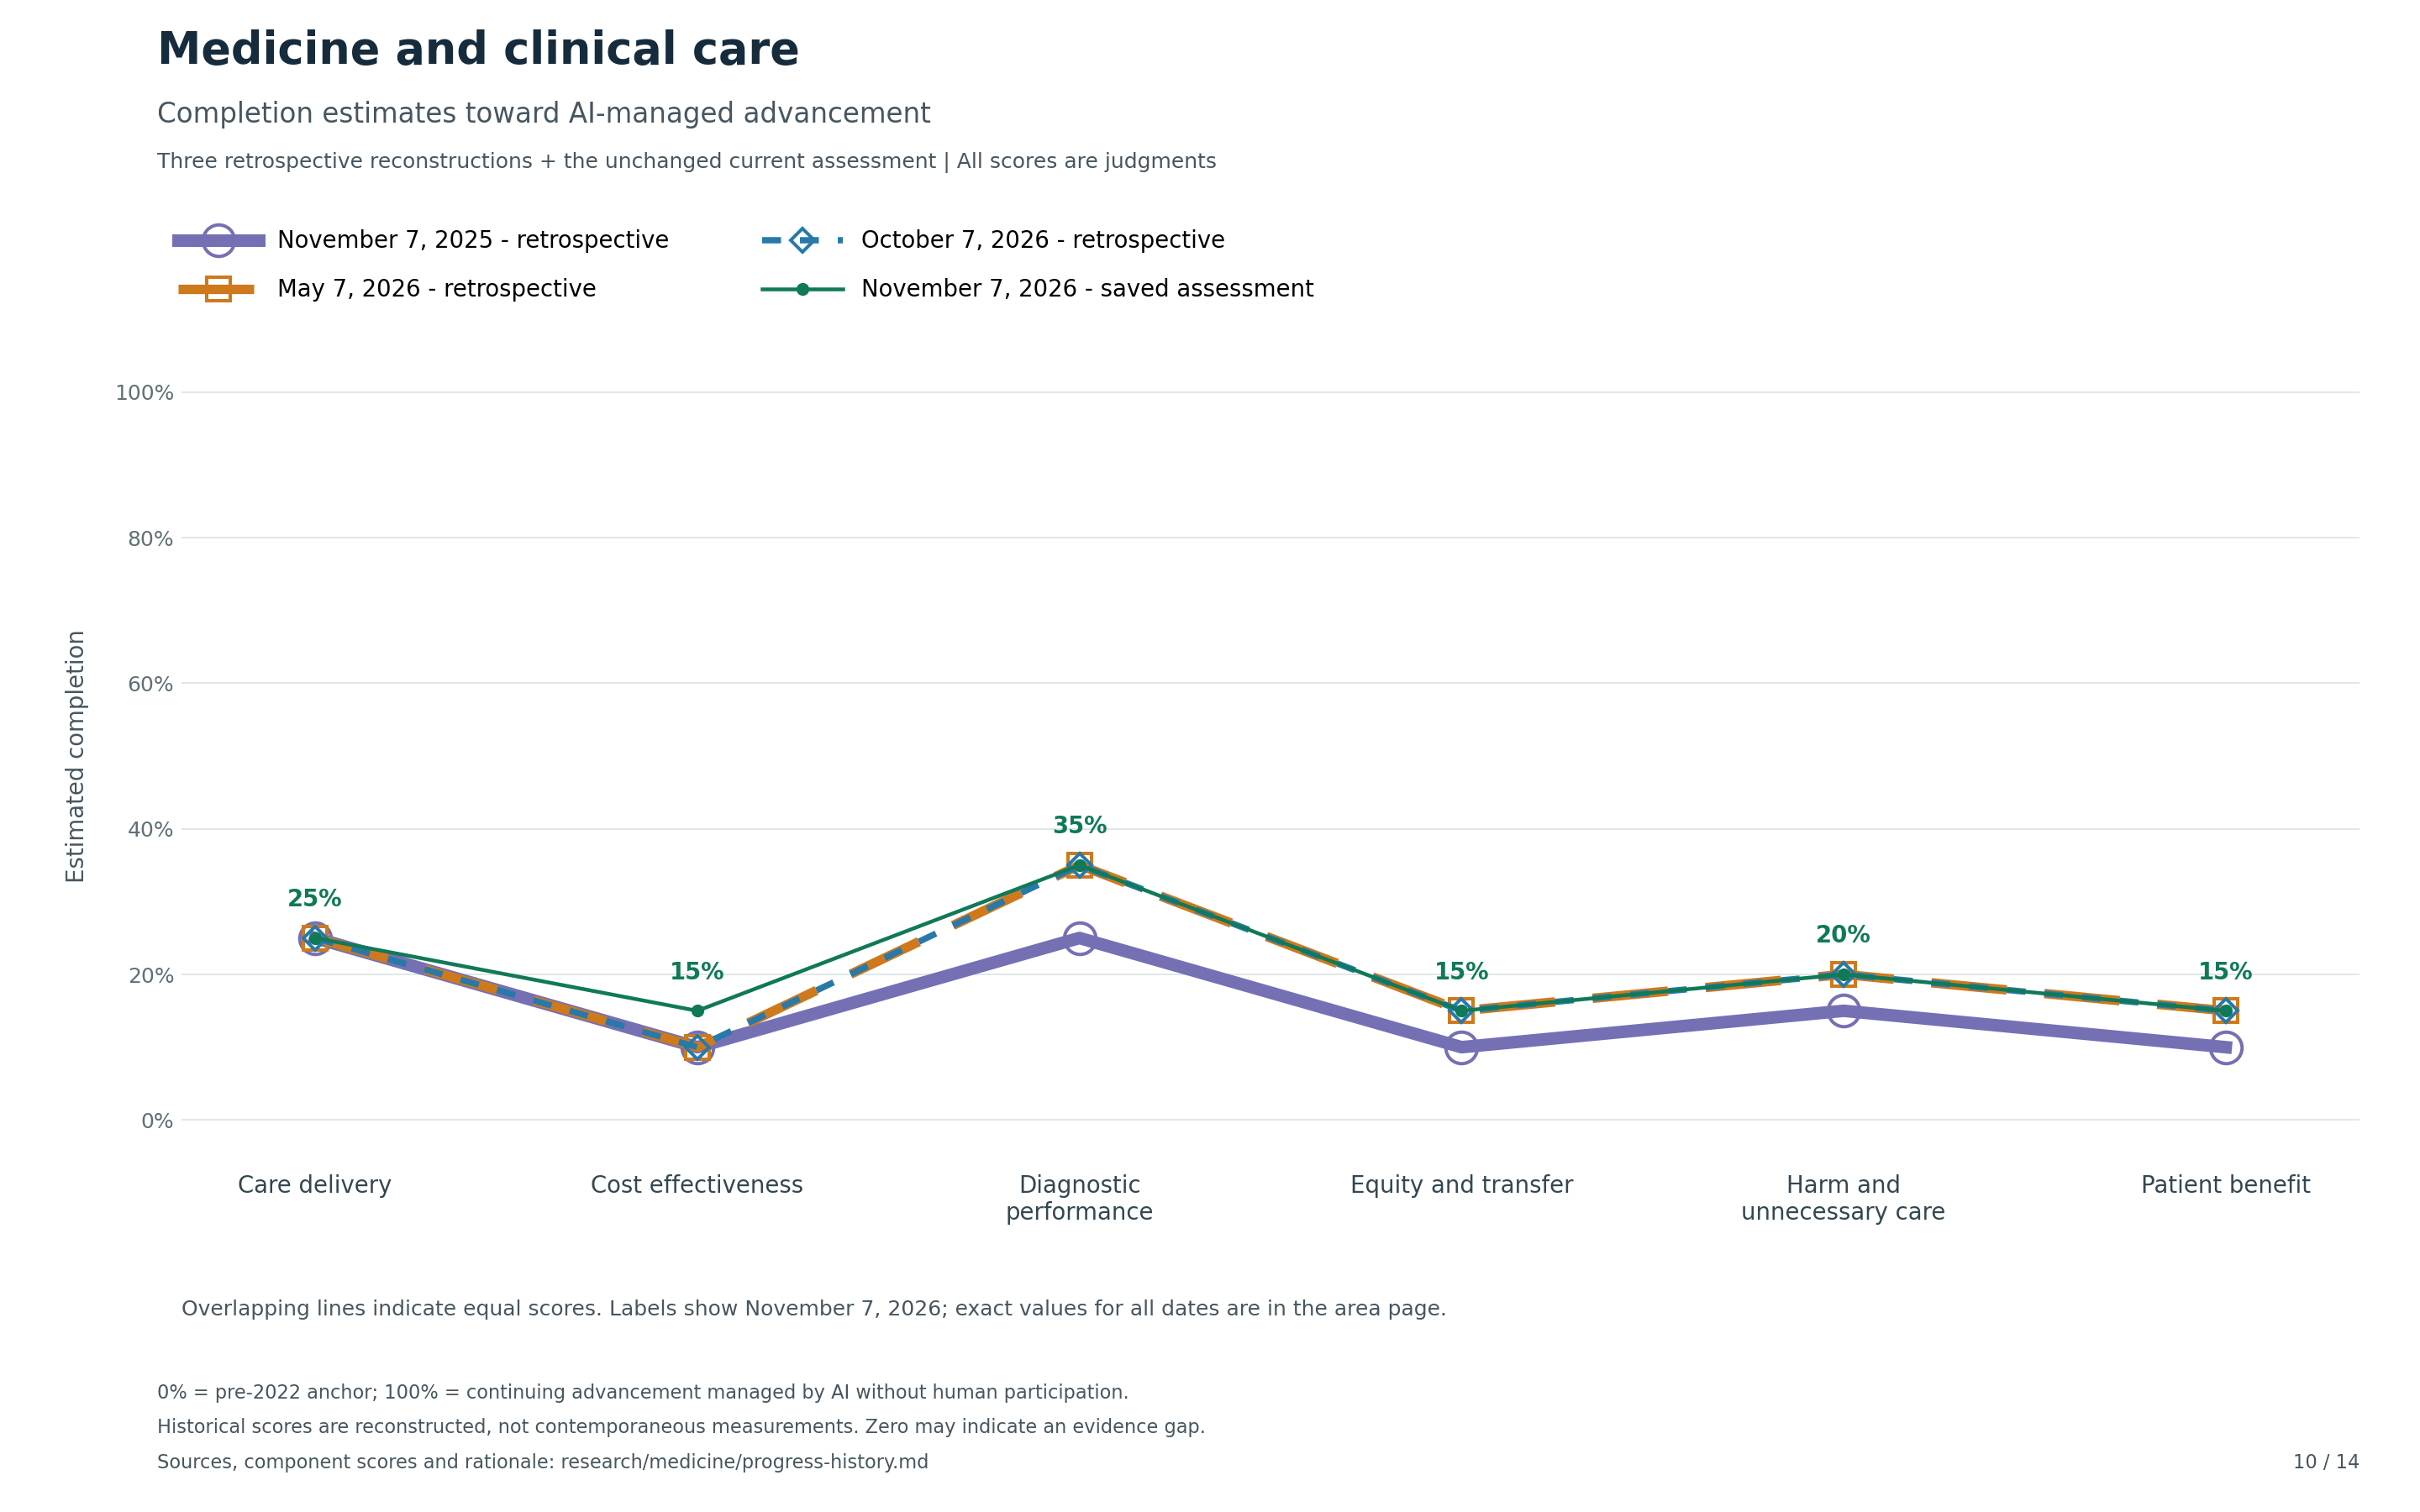
Scalable graph | Combined 14-page report
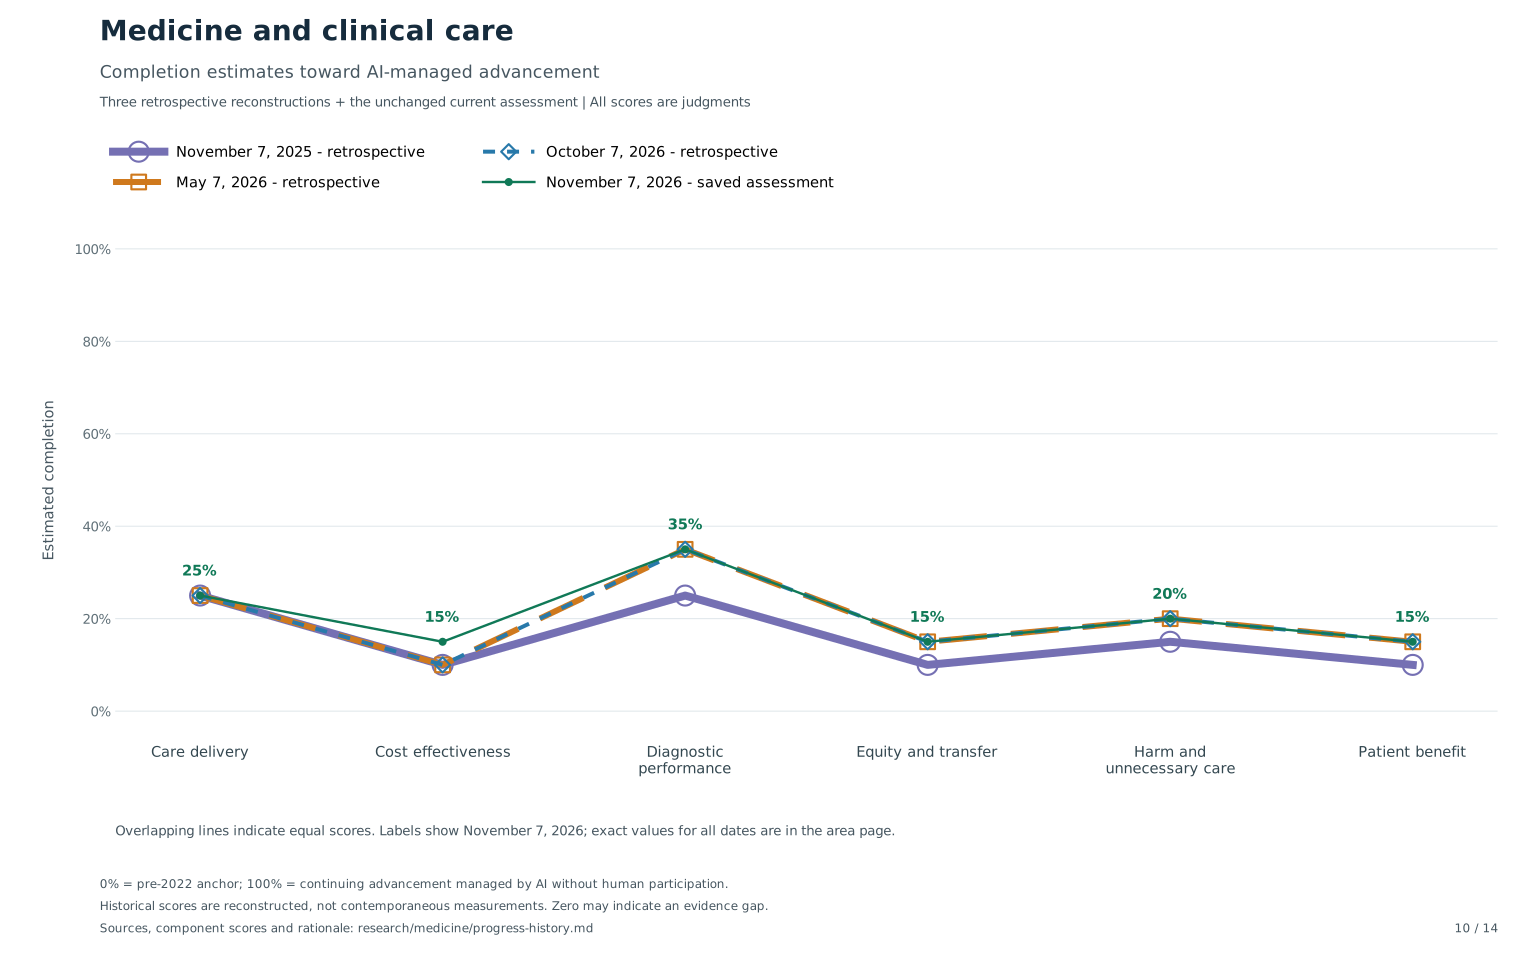
Percentage estimates
| Measurable outcome | Nov 7, 2025 (reconstructed) | May 7, 2026 (reconstructed) | Oct 7, 2026 (reconstructed) | Nov 7, 2026 (saved) |
|---|---|---|---|---|
| Care delivery | 25% | 25% | 25% | 25% |
| Cost effectiveness | 10% | 10% | 10% | 15% |
| Diagnostic performance | 25% | 35% | 35% | 35% |
| Equity and transfer | 10% | 15% | 15% | 15% |
| Harm and unnecessary care | 15% | 20% | 20% | 20% |
| Patient benefit | 10% | 15% | 15% | 15% |
Reconstruction notes and component scores
Components below are execution / breadth / agenda-setting / validation / sustained autonomous improvement, each out of 20. Their sum gives the percentage. The component values are judgments, not published statistics. Source links document evidence available by the cutoff, not the numerical estimate itself. The source section lists availability dates and version caveats. No area-wide average is calculated.
Care delivery
The workload reduction predates every cutoff. Full-pathway staff time and patient waits remain missing, so there is no inferred later gain.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 10 / 5 / 5 / 5 / 0 = 25% | masai23 |
| 2026-05-07 (reconstructed) | 10 / 5 / 5 / 5 / 0 = 25% | masai23 |
| 2026-10-07 (reconstructed) | 10 / 5 / 5 / 5 / 0 = 25% | masai23 |
| 2026-11-07 (saved) | 10 / 5 / 5 / 5 / 0 = 25% | Original score and evidence |
Cost effectiveness
Earlier workload evidence is only an economic-enabling proxy. The saved current model-based assessment adds limited evaluation credit; without a verified precise release date, it is not backdated.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 5 / 5 / 0 / 0 / 0 = 10% | masai23 |
| 2026-05-07 (reconstructed) | 5 / 5 / 0 / 0 / 0 = 10% | masai23 |
| 2026-10-07 (reconstructed) | 5 / 5 / 0 / 0 / 0 = 10% | masai23 |
| 2026-11-07 (saved) | 5 / 5 / 0 / 5 / 0 = 15% | Original score and evidence |
Diagnostic performance
Interim screening evidence supports a lower historical score. January 2026 follow-up strengthens execution and validation while staying within one screening workflow.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 10 / 5 / 5 / 5 / 0 = 25% | masai23 |
| 2026-05-07 (reconstructed) | 15 / 5 / 5 / 10 / 0 = 35% | masai |
| 2026-10-07 (reconstructed) | 15 / 5 / 5 / 10 / 0 = 35% | masai |
| 2026-11-07 (saved) | 15 / 5 / 5 / 10 / 0 = 35% | Original score and evidence |
Equity and transfer
The earlier interim trial does not establish broader subgroup transportability. Follow-up adds limited subgroup breadth without proving cross-population equity.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 5 / 0 / 0 / 5 / 0 = 10% | masai23 |
| 2026-05-07 (reconstructed) | 5 / 5 / 0 / 5 / 0 = 15% | masai |
| 2026-10-07 (reconstructed) | 5 / 5 / 0 / 5 / 0 = 15% | masai |
| 2026-11-07 (saved) | 5 / 5 / 0 / 5 / 0 = 15% | Original score and evidence |
Harm and unnecessary care
Interim safety evidence earns partial credit. The follow-up endpoint strengthens bounded execution, without resolving all downstream harms.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 5 / 5 / 0 / 5 / 0 = 15% | masai23 |
| 2026-05-07 (reconstructed) | 10 / 5 / 0 / 5 / 0 = 20% | masai |
| 2026-10-07 (reconstructed) | 10 / 5 / 0 / 5 / 0 = 20% | masai |
| 2026-11-07 (saved) | 10 / 5 / 0 / 5 / 0 = 20% | Original score and evidence |
Patient benefit
Initial detection evidence is an indirect patient-benefit proxy. Follow-up clinical characteristics broaden the evidence but still do not establish mortality or quality-of-life gains.
| Assessment date | Component points | Evidence used |
|---|---|---|
| 2025-11-07 (reconstructed) | 5 / 0 / 0 / 5 / 0 = 10% | masai23 |
| 2026-05-07 (reconstructed) | 5 / 5 / 0 / 5 / 0 = 15% | masai |
| 2026-10-07 (reconstructed) | 5 / 5 / 0 / 5 / 0 = 15% | masai |
| 2026-11-07 (saved) | 5 / 5 / 0 / 5 / 0 = 15% | Original score and evidence |
Dated sources
All sources accessed November 7, 2026. Dates below are publication or conservative availability dates, as noted.
masai23 | 2023-08-01 - MASAI interim randomized trial analysis. Interim mammography trial: reading workload and screening safety, not mortality benefit.
masai | 2026-01-31 - MASAI randomized screening trial follow-up. Screening follow-up; diagnostic and safety results remain distinct from mortality.
Future updates
Keep these reconstructions separate from subsequently recorded observations. Append new dated assessments with changed component scores and source evidence; do not silently replace historical reasoning. The shared historical-method notes describe how these snapshots were made.